
Note: This article is for educational purposes only and does not replace medical care. Anaphylaxis is a medical emergency. If you think someone is having an anaphylactic reaction, use prescribed epinephrine if available and call 911 immediately.
Anaphylaxis is the allergic reaction equivalent of a fire alarm, tornado siren, and flashing dashboard light all going off at once. It is sudden, serious, and absolutely not the time to “wait and see.” Also called an anaphylactic reaction or, in severe cases, anaphylactic shock, this condition can affect breathing, blood pressure, skin, digestion, and consciousness within minutes.
The good news is that anaphylaxis is treatable when recognized quickly. The less-good news is that it can be sneaky. Some people get dramatic hives and swelling. Others may mainly feel dizzy, nauseated, hoarse, or short of breath. In other words, anaphylaxis does not always arrive wearing a name tag.
This guide explains anaphylaxis symptoms, common causes, emergency treatment, prevention, and real-life safety lessons in plain American Englishwith just enough humor to keep things readable, not enough to make your immune system feel roasted.
What Is Anaphylaxis?
Anaphylaxis is a severe, potentially life-threatening allergic reaction that involves more than one body system or causes serious airway, breathing, or circulation problems. It happens when the immune system releases a flood of chemicals after exposure to a trigger, such as a food, medication, insect sting, latex, or sometimes no obvious cause at all.
During a typical allergic reaction, the immune system overreacts to something harmless. During anaphylaxis, that overreaction can become body-wide. Blood vessels may widen, blood pressure can drop, airways may narrow, and tissues in the lips, tongue, throat, or face may swell. That is why fast treatment matters.
Anaphylaxis Symptoms: What to Watch For
Anaphylaxis symptoms often begin within minutes after exposure to an allergen, but they can sometimes appear later. The reaction may start mildly and then escalate quickly, which is why early signs should be taken seriously.
Skin and Swelling Symptoms
Skin symptoms are common, but not guaranteed. A person may develop hives, itching, flushing, redness, or swelling. Swelling can affect the lips, eyelids, tongue, face, hands, or throat. One tricky point: a severe anaphylactic reaction can happen without hives. So, if someone says, “But there’s no rash,” do not let that sentence slow emergency action.
Breathing and Throat Symptoms
Respiratory symptoms are especially concerning. Watch for wheezing, shortness of breath, coughing, chest tightness, hoarseness, trouble swallowing, throat tightness, noisy breathing, or the feeling that the throat is closing. These symptoms are the medical version of a red-alert siren.
Heart and Circulation Symptoms
Anaphylaxis can affect blood pressure and circulation. Symptoms may include dizziness, fainting, weakness, rapid pulse, pale or bluish skin, confusion, collapse, or a sense of impending doom. That “something is very wrong” feeling can be real, not dramatic.
Digestive Symptoms
Nausea, vomiting, diarrhea, stomach cramps, and abdominal pain can also appear during an anaphylactic reaction. In children, food-triggered reactions may include prominent stomach symptoms, which can be mistaken for “something they ate” in the ordinary senseexcept this is the immune system throwing a very unsafe tantrum.
Anaphylaxis vs. Mild Allergic Reaction
A mild allergic reaction may involve localized itching, a small rash, sneezing, watery eyes, or mild hives without breathing trouble, throat swelling, dizziness, or vomiting. Anaphylaxis is different because it can involve airway symptoms, circulation symptoms, severe swelling, or multiple body systems at once.
For example, a few itchy bumps after touching a dog may be mild. Hives plus wheezing after eating shrimp is an emergency. Lip swelling plus dizziness after a bee sting is an emergency. Vomiting plus throat tightness after peanuts is an emergency. When symptoms are severe, fast-moving, or involve breathing or consciousness, treat it as anaphylaxis.
Common Causes of Anaphylaxis
Anaphylaxis triggers vary by person, but several categories are common.
Food Allergies
Foods are a major cause of anaphylaxis, especially peanuts, tree nuts, milk, eggs, fish, shellfish, wheat, soy, and sesame. Reactions can occur after eating the food, touching it, or in rare situations through cross-contact. Cross-contact means a safe food accidentally picks up an allergen from a shared surface, utensil, fryer, cutting board, or production line. Basically, the allergen crashes the party uninvited.
Insect Stings
Bee, wasp, hornet, yellow jacket, and fire ant stings can trigger anaphylaxis in sensitive people. A local swollen bump is common after a sting. Trouble breathing, dizziness, throat swelling, widespread hives, vomiting, or fainting is not “just a sting.” That is emergency territory.
Medications
Some medications can trigger anaphylaxis, including antibiotics, aspirin or nonsteroidal anti-inflammatory drugs, anesthesia-related drugs, and certain biologic medicines. Anyone with a history of medication allergy should make sure every doctor, dentist, pharmacist, and emergency provider knows about it.
Latex
Latex can cause severe reactions in some people, especially those with frequent medical exposure or certain occupational risks. Latex may be found in gloves, balloons, medical equipment, and some household items. For people with latex allergy, “just one balloon” can be a surprisingly bad idea.
Exercise, Temperature, and Unknown Triggers
Some people experience exercise-induced anaphylaxis, sometimes connected to eating a specific food before exercise. Others may react to temperature changes or have idiopathic anaphylaxis, meaning no clear trigger is identified. When the cause is unclear, working with an allergist is especially important.
Who Is at Higher Risk?
Anyone can develop anaphylaxis, but risk is higher in people with a previous anaphylactic reaction, known food allergies, insect venom allergy, asthma, mast cell disorders, or certain medication allergies. Poorly controlled asthma can make allergic reactions more dangerous because breathing is already on the guest list of problems.
Children are often affected by food triggers, while adults may have reactions from foods, medications, insect stings, or other causes. Risk can also rise when allergens are combined with cofactors such as exercise, alcohol, infection, stress, or certain medications.
Anaphylaxis Treatment: What to Do Immediately
The first-line treatment for anaphylaxis is epinephrine, also called adrenaline. Epinephrine helps tighten blood vessels, raise blood pressure, relax airway muscles, reduce swelling, and improve breathing. In simple terms, it tells the allergic chaos to sit down and stop touching everything.
Step 1: Use Epinephrine Right Away
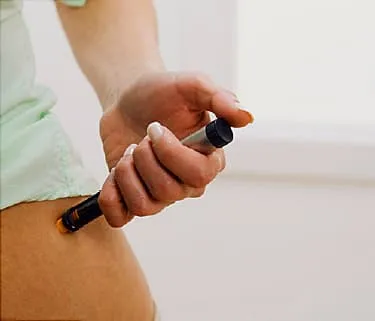
If a person has symptoms of anaphylaxis and has been prescribed an epinephrine auto-injector or epinephrine nasal spray, use it immediately according to the device instructions. Do not wait to see whether symptoms “calm down.” Delay can make anaphylaxis more dangerous.
Auto-injectors are usually used in the outer thigh and can often be administered through clothing if needed. Newer epinephrine nasal spray options may be prescribed for certain adults and children based on weight and medical suitability. The right product and dose should always come from a healthcare professional.
Step 2: Call 911
After epinephrine is given, call 911. Epinephrine is emergency treatment, not a permission slip to go back to brunch. Symptoms can return, and the person may need oxygen, IV fluids, breathing treatments, monitoring, or additional medication in an emergency department.
Step 3: Position the Person Safely
Have the person lie down with legs raised if possible, unless breathing is easier while sitting upright. Avoid having them stand or walk around. If vomiting occurs, turn them on their side to help prevent choking. If breathing or pulse stops, begin CPR if trained and follow emergency dispatcher instructions.
Step 4: Give a Second Dose If Needed
Some reactions require a second dose of epinephrine if symptoms continue or return. People at risk are often advised to carry two doses because anaphylaxis is not famous for checking whether one device is convenient.
What About Antihistamines, Inhalers, or Steroids?
Antihistamines may reduce itching or hives, and inhalers may help wheezing in people with asthma, but they do not replace epinephrine. They do not reliably treat throat swelling, severe breathing problems, or dangerously low blood pressure. Steroids may be used in medical settings, but they work too slowly to be the main emergency treatment.
The rule is simple: for suspected anaphylaxis, epinephrine first. Other treatments come after, not instead.
Diagnosis and Follow-Up Care
Anaphylaxis is usually diagnosed based on symptoms, timing, and exposure history. In some cases, clinicians may order blood tests such as serum tryptase soon after the reaction, but emergency treatment should never wait for a lab result.
After recovery, follow-up with an allergist is important. Allergy testing may help identify triggers, clarify risk, and guide prevention. The allergist may recommend carrying epinephrine, creating an emergency action plan, wearing medical identification, or considering treatments such as venom immunotherapy for insect sting allergy.
How to Prevent Anaphylaxis
Prevention begins with knowing your triggers. For food allergies, read ingredient labels every time, ask restaurants detailed questions, and be cautious with buffets, bakeries, shared fryers, and sauces. “It probably doesn’t have nuts” is not a food safety strategy; it is a plot twist waiting to happen.
People with insect sting allergy should avoid walking barefoot outdoors, drinking from open cans outside, wearing strong fragrances near stinging insects, and swatting aggressively at bees or wasps. Calmly moving away is usually smarter than entering combat with a creature that brought a tiny sword.
For medication allergies, keep an updated allergy list and share it before any prescription, procedure, surgery, dental work, or imaging test. For latex allergy, request latex-free medical supplies and alert healthcare teams before appointments.
Creating an Anaphylaxis Action Plan
An anaphylaxis action plan explains what symptoms to watch for, when to use epinephrine, when to call 911, and who should be contacted. Children should have plans at school, daycare, camps, sports activities, and relatives’ homes. Adults should consider sharing the plan with coworkers, travel companions, gym partners, and close friends.
A strong action plan includes the person’s allergens, medication names and doses, emergency contacts, doctor information, and device instructions. Practice matters. In an emergency, nobody wants to learn an auto-injector while their brain is buffering like slow hotel Wi-Fi.
Living With Anaphylaxis Risk
Living with anaphylaxis risk can feel overwhelming at first, but preparation reduces fear. Carry epinephrine consistently, check expiration dates, store devices at recommended temperatures, and replace them after use or expiration. Keep one set at home and carry another when away, if your clinician recommends it.
It also helps to develop polite but firm scripts. At restaurants: “I have a severe allergy. Can you check whether this dish contains shellfish or could have cross-contact?” At parties: “That looks amazing, but I need to confirm ingredients before I try it.” At work: “Please don’t feel awkward. My allergy plan is boring on purpose, and boring is exactly what we want.”
When to Seek Emergency Help
Call 911 immediately if an allergic reaction includes trouble breathing, throat tightness, tongue or lip swelling, fainting, dizziness, confusion, widespread hives with vomiting, or symptoms involving multiple body systems. Also seek emergency care after using epinephrine, even if the person improves.
A second wave of symptoms, called biphasic anaphylaxis, can happen after the first reaction seems to settle. Medical observation helps catch returning symptoms before they become dangerous.
Practical Experiences and Real-Life Lessons About Anaphylaxis
Real-life experience with anaphylaxis often teaches lessons that sound obvious only after the fact. The first is that people commonly underestimate early symptoms. Someone may say, “My throat feels weird,” “I just feel off,” or “My stomach hurts,” and the room may not immediately understand the seriousness. In families managing food allergies, that vague first sentence can be the beginning of the emergency timeline. The best habit is to treat unusual symptoms after a known exposure with respect, not debate-club energy.
Another common lesson is that epinephrine hesitation is real. People may worry they are overreacting, using the device incorrectly, wasting an expensive prescription, or causing side effects. But anaphylaxis is not the moment to audition for Most Calm and Casual Human. Epinephrine is prescribed because the risk of untreated anaphylaxis is far greater than the temporary jitters, fast heartbeat, or shakiness that may follow the medicine. Many allergy families create a simple rule: when in doubt and symptoms suggest anaphylaxis, use epinephrine and call 911.
Food situations bring their own adventures. A person with a peanut allergy may be careful with cookies but forget that sauces, desserts, protein bars, cereals, and shared kitchen tools can be risky. Restaurant staff may be helpful, but communication needs to be clear. Saying “I’m allergic” is stronger than “I don’t like.” Saying “severe allergy” is clearer than “sensitive.” The goal is not to be dramatic; the goal is to prevent a medical emergency from being treated like a garnish preference.
Schools, camps, and workplaces also show why planning matters. A child’s epinephrine should not be locked in a mystery cabinet known only to someone who went home early. A coach, teacher, babysitter, or bus driver may be the first adult present when symptoms begin. Training, written plans, and accessible medication turn panic into action. The same applies to adults: coworkers do not need your entire medical history, but one trusted person knowing where your epinephrine is can be incredibly useful.
Travel adds another layer. People at risk for anaphylaxis often learn to pack extra medication, keep epinephrine in carry-on bags, research local emergency numbers, bring safe snacks, and translate allergy cards when traveling internationally. It may feel like overplanning, but compared with explaining a cashew allergy through hand gestures at midnight, preparation is a luxury.
Finally, emotional experience matters. After anaphylaxis, people may feel embarrassed, anxious, angry, or exhausted. Parents may become hypervigilant. Adults may avoid restaurants or social events. That reaction is understandable. The goal is not to live in fear; it is to build routines that make safety feel normal. With an allergist, a clear action plan, reliable epinephrine access, and honest communication, many people with anaphylaxis risk live active, social, delicious livesjust with more label reading and fewer mystery cupcakes.
Conclusion
Anaphylaxis is a fast, severe allergic reaction that can affect breathing, circulation, skin, digestion, and consciousness. Common causes include foods, insect stings, medications, latex, exercise-related reactions, and unknown triggers. The most important treatment is prompt epinephrine, followed by emergency medical care. Antihistamines and inhalers may help certain symptoms, but they are not substitutes for epinephrine.
The best defense is preparation: know your triggers, carry prescribed epinephrine, teach others how to help, create an action plan, and follow up with an allergist. Anaphylaxis is serious, but with the right plan, it becomes manageable. Think of preparation as a seat belt: you hope you never need it, but you will be very glad it is there.
SEO Tags




